

The dead teach the living

"Charlise Suzanne Felts passed away on Friday, Feb. 27, 2015, in Austin, Texas, surrounded by family. She was 67 years old. Suzanne was born on Nov. 18, 1947, in Mount Holly, New Jersey, to Frederick Charles Starn and Charlotte Louise Gregg. She was raised in Chestnut Hill, Pennsylvania, and received a degree in fine arts from Finch College in New York. ...
"Suzanne was passionate about nutritional healing, animals and the arts. She was an equestrian, loved travel, and found fulfillment and joy in caring for others. …”
And then she gave her lifeless body to science, to medical students who would learn from her bones and flesh and muscle and sinew to heal the living. She became their silent teacher.
***
In the winter of 2014, Linda Baker-Webber, coordinator of the Body Donation Program at UT Health San Antonio, received a call from Suzanne Felts. She was dying, Felts explained, and wanted to know more about the program.
“She told me she was interested in it, was considering it, that she had cancer and this was where she wanted to be, but she wanted to meet the people who would be taking care of her,” Baker-Webber said. “That’s highly unusual, to meet a donor, but it was very important to her. So I relayed that to my director.”
After four years as director of the program, Omid Rahimi, Ph.D., had never met a potential body donor, and he didn’t want to start now.
“Our program is anonymous,” said Dr. Rahimi, associate professor of cellular and structural biology who also directs the Human Anatomy Program. “There’s a balance we have to find. We have to separate the fact that this was a person from the fact that this [cadaver in the lab] was a tool, a machine. Otherwise it’s not easy to do what we do. The student has to be able to say, I have a job to do, I have to learn. For me, if I know the person, it would be more difficult.”
But Felts was insistent and continued to call.
“I told [Dr. Rahimi], if you speak with her, you’ll want to meet her,” Baker-Webber recalled.
On her own terms
By all accounts, Suzanne Felts was one of a kind, a child of the universe. She was highly opinionated and stubborn, especially when it came to her health. She was intensely spiritual, if not overtly religious. She was a social being and loved meeting people. All the wonders of nature fascinated her. She reveled in the beauty of art, as both a collector and a
pastel artist.
And deadly cancer ran in her family.
Suzanne grew up in somewhat privileged circumstances in New Jersey and Pennsylvania. Her parents were well off, and she was proud to trace her ancestors back to the Mayflower. When she was 19, she married and moved to a farm in the Blue Ridge Mountains of Virginia, where she had four children before the marriage ended in divorce.
Then it was on to Las Vegas, where she lived for decades and where her interest in nutrition blossomed. She opened a health food business and was keen to learn all she could about natural healing. She eventually met and married a Texan, moving first to Arkansas, then Marble Falls, Fredericksburg and finally Austin.
Two of her sons, twins Massie Wallace and Teddy Wallace, remember her as a free spirit, naturally inquisitive, a jokester who loved April Fool’s Day, an animal lover.
Massie’s wife, Anna, recalls Suzanne feeding all the stray dogs and cats in her neighborhood.
“In fact, there was a family of possums that were welcome on her back porch. She’d feed them every night, even though they’d fight with her own cats.”
But one interest overshadowed all others.
“Nutrition was basically her life,” Massie said. “In terms of taking care of herself, she always wanted to go the most natural route. She had a strong spiritual connection to a higher power. She was very much a person of mind over matter. Meditation, positive thinking, salt lamps, calm relaxing music. Her environment was most important.”
But by 2014, she had already faced seven bouts with breast cancer dating back 34 years. After finding a lump under her arm and learning that cancer had spread throughout her lymphatic system, Suzanne knew the end was near.
She always met the disease head on and on her own terms.
She was absolutely opposed to chemotherapy and never had the treatment, her sons said. She took a variety of vitamins, minerals and exotic supplements. She kept notes over the years of what foods to eat, what not to eat, what exercises to perform. She kept a daily “Life Plan” that outlined a health routine, with entries such as “Put chamae rose under my tongue” and “Eat 2 tablespoons sprouted raw red wheat.”
She didn’t believe in going to traditional doctors unless she absolutely had to, and even then “she’d just put them in their place” if she felt they were wrong, Teddy said. “She’d just debate them, question everything they did.”
And she remained whimsical about life, Massie said.
“Even when she was going to die, she could laugh at her cancer,” he said. “She wouldn’t let it control her. She didn’t pretend it wasn’t there, but she could laugh about it. At one point they put some sort of dye in her to see where the cancer was, and she said, ‘I just lit up like a Christmas tree. It was everywhere!’”
She began thinking of donating her body to science.
“She didn’t want to pass away, but she had accepted it,” said her daughter-in-law, Anna. “It was hard for her to accept that she wouldn’t be around to help people. She saw this as a way for her to express herself and help people learn from her when she’s gone.”
And to Suzanne’s way of thinking, Anna continued, meeting the people she was going to give her body to was an absolute requirement.
“She didn’t give them an option,” Anna said. “She wasn’t going to gift them with her body unless they met her. She said she wanted to see where she was going after.”
The ultimate gift

human body with teaching assistants and fourth-year medical students Dawn Zhao and Matthew McMahon.
Dr. Rahimi is profoundly grateful to body donors and their families.
“The primary benefit of doing dissections on a cadaver is to learn the intricacies of the human body and the beauty of how the body works, how the body functions so well most of the time for so many years,” he said. “It’s the science behind what the physicians will use to treat his or her patients.”
The university accepts around 200 bodies per year. Donors must be 18 and there are no costs involved. (It’s illegal to pay for body donations or parts.) There are only a few exclusions. Donors can’t be obese or emaciated, and they cannot have any communicable diseases or cancer that has metastasized in the abdomen to multiple organs.
The cadavers are used in anatomy classes by first-year medical students, dental students who focus on head and neck dissections, physical therapy students, occupational therapy students, physician assistant students, graduate and biomedical engineering students.
Anatomy workshops for EMT and AirLIFE workers also utilize cadavers, as do physicians learning new surgical techniques or procedures and residents who can practice procedures before treating patients.
Yet the cadavers represent so much more, Dr. Rahimi said.
“This is [the students’] first experience of being exposed to a person who has passed away and recognizing the value of the gift they have received, recognizing the altruistic nature of the person donating themselves for the greater good of humankind,” he said. “I think that really puts in context the career they’re about to embark upon.
“The value of giving and the spirit of love and caring for other people is what they’re gaining. There’s no other way to teach that empathy, that recognition of the importance of patient care, of respect and dignity. The cadaver is their first patient. The student will know more about this person than any other patient they will ever have because they’re going to fully learn the intricacies of this body they’re dissecting.”
Body of knowledge
Despite his reluctance, Dr. Rahimi, along with Linda Baker-Webber, met Suzanne on Dec. 29, 2014.
“She was bubbly. She was a beautiful woman,” Baker-Webber recalled. “To look at her, she was the picture of health. She was warm and very receptive, laughing, smiling, in very good spirits. She was a very joyful woman to meet, but she knew her fate.”
Dr. Rahimi said the meeting turned out to be “one of the most enlightening experiences for me.”
Suzanne was “prolific in telling others about her interest in health and nutrition,” he added. “She wanted to tell that to as many people as possible. And the information she had gained about her body through her research, her experiences with health and her disease, she wanted to give her body as a body of knowledge to us to learn from.
“She was 100 percent interested in, ‘How else can I help? Even in my death I want to be able to help. Here’s my body. Are you going to be able to use it?’”
Anna recalled the day of the meeting.
“I remember her getting ready for that interview,” she said. “She spent hours getting ready to go meet these people. It was really important to meet them and look alive. She said she didn’t want to look sick or for them to remember her as looking sick. She left the house in heels and all made up.
“She didn’t want to just be a body. I know it’s the Body Donation Program. But she said she wanted to give her life to them. I think she accomplished that.”
Suzanne left the meeting comfortable with the surroundings and with her decision to donate her body. Sixty days later, on Feb. 27, 2015, she was dead.
Gone, but not forgotten
Toward the end of each academic year, the Body Donation Program holds a solemn interment ceremony to bury the remains of donors. Faculty, staff, students and the families of the donors gather as bagpipes sound the familiar notes of Amazing Grace, an AirLIFE helicopter performs a flyover and buglers play Taps. Always, students representing each of the anatomy classes talk about the life lessons learned through those who gave themselves as the ultimate gift.
Last April, occupational therapy student Kathryn Crane addressed the gathering.
“There will not be a moment that goes by in our careers that we won’t think about what a blessing it was to have this hands-on experience,” she told the families. “Your loved ones have helped shape us as clinicians, but ultimately because of their generosity, they have helped those that we will treat. The gift they provided us is one that will continue to give and will never be forgotten.”

Supporting a new generation of scientists

Vaccines work because they teach the body to remember—and attack—a particular disease. So Elizabeth Leadbetter, Ph.D., is studying how to enhance the immune system’s memory to identify and attack a disease such as cancer.
Lipid-containing nanoparticles activate B cells and natural killer T (NKT) cells to work together to amplify the body’s memory of the invading disease. If she can harness this process, the body’s memory of the invading disease could be enhanced, which could lead to the detection of precancerous changes in the body and prevent the spreading of the disease, Dr. Leadbetter believes.
“This funding will allow me to apply an approach I had been using to develop a vaccine for an infectious pathogen and apply the same idea to developing an anti-cancer treatment,” said Dr. Leadbetter, associate professor of microbiology and immunology. “If this is as successful as I hope, it should lead to a completely new direction for my lab and will eventually help to make us competitive for other funding opportunities in the cancer arena. I am eager to see if our approach can make a lasting impact in the area of cancer immunotherapy.”
Dr. Leadbetter was one of three junior faculty members in the School of Medicine selected to receive $450,000 over the next three years from the Max and Minnie Tomerlin Voelcker Fund. The money will be used to develop innovative lines of research to make preliminary discoveries that may result in attracting National Institutes of Health-funded research to the city. Xiao-Dong Li, M.D., Ph.D., assistant professor of microbiology, and Kexin Xu, Ph.D., assistant professor of molecular medicine, were also recipients of $450,000 to advance their work.
“Voelcker Fund awards help junior scientists to establish a track record of success,” said William L. Henrich, M.D., MACP, university president. “The focus of our awards in 2016 is cancer, a disease that is, in its complexity, a thousand diseases.”
Dr. Li’s research focuses on the DNA of tumors. He has discovered a molecular pathway the immune system uses to recognize and attack abnormal DNA. A vaccine to boost this pathway could be very effective in fighting cancerous tumors, in addition to fending off viral threats, he said.
Dr. Xu seeks to understand the link between cancer and metabolic disease such as obesity and diabetes. She focuses on epigenetics, the study of biological processes that switch genes on and off without altering the genetic code itself. Epigenetic changes may be prompted by the environment, diet, stress, aging and other factors.
“The Voelcker Fund is impressed with the quality of the investigators and their research,” said Banks M. Smith, a Voelcker trustee. “We know strides will be made to help find cures for cancer.”
Since 2007, the Voelcker Fund has given more than $18 million to the university. In addition to the Young Investigator Awards, the fund also supports other university initiatives, such as the Voelcker Biomedical Research Academy, which provides an immersive biomedical research education and college preparatory program for San Antonio-area high school students.
Dr. Leadbetter pointed out that in a time of declining government support for scientific research, funding by philanthropies such as the Voelcker Fund is vital.
“Without it,” she said, “we could lose an entire generation of scientists.”

And then there was light
Pat Johnson vividly recalls his near-death experience after a boating accident on the Blanco River nearly six years ago. He speaks of that day in reverential tones, of being “in the presence of God” and “at the edge of heaven.”
And he recalls telling his doctor about the experience.
“He basically laughed at me,” Johnson said. “He chuckled and said, ‘Oh, it’s just your frontal lobe shutting down that causes you to have this euphoric feeling and you hallucinate.’ I told him that, no, this wasn’t a hallucination, this wasn’t a dream. ‘It was as real as me standing here talking to you.’ At that point I thought, I don’t care what anyone tells me.”
While near-death experiences are common, so too is the reaction by Johnson’s physician, said Deborah James, M.S.N, RN, CNS, CCRN-K, a clinical assistant professor in the School of Nursing and recognized expert in end-of-life care and near-death experiences.
James, who in 2009 co-authored and co-edited the first compilation of research on the subject, Handbook of Near-Death Experiences: Thirty Years of Investigation, said one in three people who have a close brush with death report a near-death experience.
And James is on a mission to make sure health care professionals, nurses in particular, know how to listen and respond when a patient recounts such a profound experience.
 Over her decades-long career, most spent in intensive care units or other critical care settings, James has met and listened to dozens—if not hundreds—of near-death experiencers, or NDErs. All the stories are different, but there are many common threads.
Johnson’s story begins when he was kayaking with a friend on a swollen river. He was suddenly sucked into a pipe underneath a low-water crossing. Under water, he fought to pull himself out but couldn’t. He was drowning, and soon lost consciousness.
Still, he said, “I felt like I knew where I was at, and I was in a good place. And I thought, I haven’t been that great a person, but I felt like I was in heaven, in the presence of God.”
He sensed “a multitude” of souls around him.
“I didn’t see them but I felt a part of them. I knew they were there.”
And then there was light, “like looking into a kaleidoscope,” Johnson said. “I wanted to get to the light, go to the light.” He was at peace, surrounded by love. “It was beautiful. If I had stayed there, I would’ve been fine with it.”
But somehow the current swept Johnson through the pipe and deposited him downstream, where his friend pulled him to safety and resuscitated him.
As with Johnson’s experience, a common thread is the bright light at the end of a tunnel or hallway, and an extraordinary sense of love and serenity.
“This is not any laughing matter,” James said. “This is not one of those things that people dream up. This is not a dream.”
Years ago, James said, a patient in ICU became irate after he was resuscitated.
“He said, ‘I can’t believe you people made me come back.’ And everybody is like, ‘We did our job. He must be confused.’”
It’s not unusual, she said, for health care professionals and others to consider NDErs to simply be confused, disoriented or trying to get attention.
“What happens many times is those patients get medicated,” James continued. “Health care providers will often order medications because they think the patient is psychotic. Often veterans are treated as if they’re suffering from PTSD.”
So it’s normal for NDErs to be a bit leery of communicating the details of what happened.
“Some people think you’re crazy,” said Johnson, the near-drowning victim. “Almost immediately you develop a sense of who you can talk to about it and who you can’t.”
And if a near-death experiencer is afraid to tell his story or it’s casually dismissed, the person feels rejected, becomes more isolated, more apt to question the experience, and more prone to have self-doubts and fears. They may keep the experience bottled up inside for years.
James, who teaches a variety of courses at the Health Science Center, introduces near-death experiences and the proper response from health care providers whenever she can: while talking about anything from end-of-life or palliative care and hospice to patients coming out of resuscitation.
“As nurses,” James said, “we should listen without judgment. You can tell the difference between someone who is confused and really struggling and someone who’s had a near-death experience.”
More and more health care professionals are responding positively, James said. So are students.
Brittany Jasso, a nursing student who will graduate in May, said nurses should always be open to what near-death experiencers are saying.
“You should ask them to tell you more, like, what did you see, what did you feel,” she said. “I’m not there to minimize their feelings. I’m not there to judge them.”
Despite the skepticism of his doctor, Johnson continues to be enthusiastic about sharing his story, meeting others with similar experiences and seeking a deeper meaning as he gets on with life. And he thinks health care providers are crucial, especially in the beginning, in that search for meaning.
After all, he said, “a near-death experience is more about living than it is about dying.”

Healing in flight
Photo courtesy of the U.S. Army. Photo by Sgt. Duncan Brennan, 101st Combat Aviation Brigade public affairs.
Getting wounded soldiers the fastest, most skilled emergency medical care possible and transporting them to forward units or hospitals has long been a priority in warfare. To that end, the Army turned to the Long School of Medicine and its expertise in emergency care.
After a yearlong pilot project in 2011, the Department of Emergency Health Sciences was selected by the Army in 2012 to train all Army flight medics. A five-year contract calls for the university to provide four paramedic certification courses and four critical care transport courses per year for flight medics. This year, due to the success of the program, the department will offer six courses.
It’s a charge that Lance Villers, Ph.D., LP, associate professor and chair of the department, doesn’t take lightly.
“All of these soldiers are EMTs who were trained at Fort Sam,” Dr. Villers said, explaining that San Antonio’s Fort Sam Houston is the center for all medical training for the Army. “Many of them have been deployed and have combat experience. Then all of the designated flight medics for the Army are brought back here for our training.”
Intensive classroom instruction covers anatomy/physiology, patient assessment, advanced airway procedures, cardiovascular emergencies, medical and trauma emergencies, EMS operations, hospital clinicals and EMS field practicums.
“When they finish our program, they’re prepared for national certification for paramedic,” Dr. Villers said. And then immediately “they start an eight-week, critical care transport program. This is even more advanced training that prepares them for a national certifying program to be flight paramedics.”
Rotations include the operating room for airway procedures, various intensive/critical care wards, the burn unit, cardiac catheterization lab, neonatal intensive care unit and pediatric intensive care unit, and obstetrics for delivering babies. This phase emphasizes the development of critical thinking skills.
All clinical time is done at civilian hospitals and specialty clinics in the San Antonio area.
Lt. Col. Neil B. Davids, M.D., LTC, Critical Care Flight Paramedic Program director at Fort Sam Houston, said the program's quality is reflected in its high first-time pass rate on the National Registry Paramedic certification exam—nearly 20 percent higher than the national average.
“Getting the clinical experience, both in the hospital and riding out with various EMS agencies, has been crucial in meeting our goal of having paramedics with critical care training [available] to the fighting force,” he said.
Dr. Villers finds significance in the work his department does for the Army.
“This training makes a difference for soldiers,” he said. “Once these soldiers complete our training, they go right back out to their deployments, many to a combat zone. And they’ve been given a new set of tools, of knowledge, to save people’s lives. We’re proud to be part of that.”

Beyond words
One couple's commitment to education has changed countless lives

Health Science Center students through scholarships since 1999.
*This story has been updated to reflect the current value of the Longs' contributions to UT Health San Antonio, now totaling more than $61 million. See full story here.
One by one, the students line up to write notes of gratitude to a couple who many haven’t met but who has made a profound impact on their lives. Many say that “words can’t describe” their feelings, but they try. They pen their notes, adding personal stories and details sprinkled with expressions such as “amazing,” “inspiring,” “generous.”
They are messages for Joe R. and Teresa Lozano Long, and the occasion is the annual lunch for the Austin philanthropists who have changed the lives of countless Health Science Center students and, by extension, the thousands who have benefitted from the health care provided by those who have received and will receive scholarships from the Longs.
The Longs have supported Health Science Center students through scholarships since 1999. In 2008, the couple made a gift of $25 million to establish the Joe R. and Teresa Long Scholarship Research and Teaching Fund endowment, which resides in the Office of the President. As of August 2015, the market value of the Long fund exceeded $28 million. *In February 2017, the couple contributed an additional $25 million, bringing the total value of their giving to more than $61 million.*
Earnings from the fund were awarded in scholarships to 50 students in 2015-16, including medical, nursing, physician assistant and graduate students. In addition to scholarships, the Long fund also supports the creation of new chair endowments for faculty. So far, the fund has established the Long Distinguished Chair in Metabolic Biology, held by Yuguang (Roger) Shi, Ph.D. It also is building a new Long Distinguished Chair in Diabetes. It will create a new chair every few years, in perpetuity. The fund also supports investments in research.
The Longs routinely receive countless thanks from their scholars, but the couple has a message for them too: “Being a health care provider is a rewarding profession,” Mr. Long said. “You’ve got your whole life ahead of you and when you finish, you’ll be glad you did it.”
Travis Hayden, a first-year medical student and Long Scholar, remembers “being in a state of disbelief for almost a whole month after hearing the news” that he had been selected for a scholarship. He said the Longs have left a legacy that will live on for generations.
“I hope the Longs are assured that their investment in our education has impacted students in a special way,” he added, “inspiring us to carry on the hard-working, selfless and empathetic values that embody their legacy.”
Jill Heisler, a Long Scholar, is a student in the joint M.D./Ph.D. program. She finished the graduate studies portion of the program in 2014 with a Ph.D. in pharmacology/neuroscience and received her medical degree in May.
“Thanks to various funding sources such as the Long scholarship fund, I am able to get through my eight years of medical and graduate training without an insurmountable amount of debt—without any debt, in fact,” Heisler said. “That is an incredible gift that I am truly grateful for.”
The couple has a passion for education and the arts. He was a highly successful lawyer, having attended UT Austin School of Law, and was a banker; she was the first in her family to attend college and went on to earn her doctorate in education from UT Austin. Both come from working-class backgrounds, and both are proponents of sacrifice and hard work.
Health Science Center President William L. Henrich, M.D., MACP, addressed the couple at the April 15 appreciation lunch: “When the next chapters are written and the history of our UT Health Science Center San Antonio is chronicled, one chapter will certainly be devoted to you, Joe and Terry, for all that you have done to transform and enrich our university and the education of students in San Antonio and South Texas.”
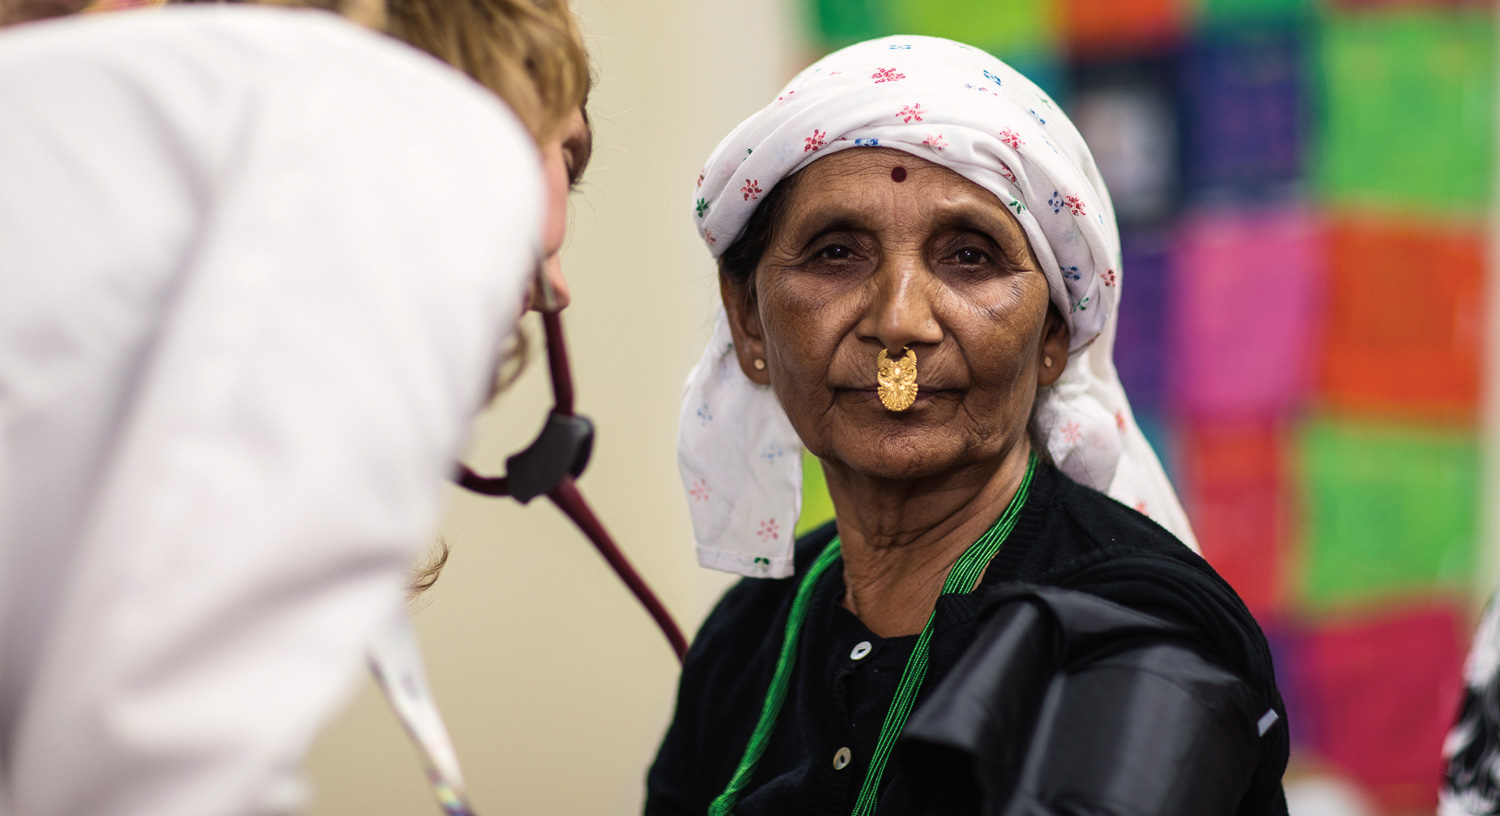
The 'lost' population
PHOTOS BY JOEL SPRING
Student-run clinic brings health care to those fleeing violence and persecution

In the triage area, second-year medical student Fadi Al-Asadi, who was born and raised in Iraq and whose first language is Arabic, bends down to try and wake a sleeping toddler in a stroller. “Bon jour,” Al-Asadi says jovially to the French-speaking child from Cameroon in West Africa.
Across the way, nursing student Christina Potts is busy processing new patients. There’s a three-generation family from Burma, followed by a couple and their children from Bhutan. Next up is an elderly, white-bearded man from Iran wearing a woven, white prayer cap. The “waiting area”—chairs lined up and down the hallways—is crowded with refugees, each with a personal story of fleeing violence, persecution and war. The place is teeming with sound and color, the cadences and rhythms of world languages and bright ethnic dress from Africa, the Middle East and the Indian subcontinent.
And they keep coming through the doors of the makeshift clinic at St. Francis Episcopal Church on Bluemel Road, near the South Texas Medical Center. Sniffling babies, stooped men and stoic women, all seeking health care.
This is a San Antonio health clinic like no other. It is the Health Science Center’s student-run, free San Antonio Refugee Health Clinic, a blessing for refugees and a teaching tool without parallel for the students who volunteer.
Back in triage, Al-Asadi, who was a teenager in Baghdad when the U.S. invaded Iraq in 2003, is moving from patient to patient, listening, learning, treating. He spent a year in Syria as a refugee himself before coming to the States in 2008, and so has “a personal connection” to the patients.
“Compassion is about 90 percent of the whole deal,” he said.
[bgsection pex_attr_title="" pex_attr_subtitle="" pex_attr_undefined="undefined" pex_attr_style="section-dark" pex_attr_bgcolor="000000" pex_attr_image="" pex_attr_imageopacity="1" pex_attr_bgimagestyle="static" pex_attr_titlecolor="ffffff" pex_attr_textcolor="ffffff" pex_attr_height="150"]
Governments create borders. Diseases do not follow those borders. If we’re not educating our students in global health, we’re doing a great disservice.”
—Andrew Muck, M.D., medical director for the Refugee Health Clinic
[/bgsection]
A helping hand
The Refugee Health Clinic, which operates weekly, began in 2011, building on a School of Nursing effort. It is one of five student-run clinics that operate through the Center for Medical Humanities & Ethics, and is by far the most interprofessional with medical, dental, nursing and physician assistant students and faculty advisers.
It is estimated that 4,000 to 5,000 refugees live in a small area off Wurzbach Road in northwest San Antonio, within three miles of the Health Science Center. About 1,000 arrived in 2014 alone. They hail from dozens of countries, including Iraq, Cuba, Burma, Afghanistan, Iran, Bhutan, Congo, Somalia, Eritrea and Ethiopia.
Most refugees who are resettled in the United States are given temporary health benefits by the federal government that typically run out after six to eight months. Many of those who rely on the student-run clinic have no insurance, few resources and are without regular medical care. The Refugee Health Clinic plays a vital role in filling this gap, treating an estimated 500 patients a year.
“It’s really a lost population,” said Victoria Petty, one of the nursing student leaders at the clinic. “When you think of refugees, you think of New York or Miami. You think of these big portals of the U.S., not San Antonio. But we really have a population here that’s not even recognized.”
Patients mirror those from any outpatient clinic, with general health concerns, said Al-Asadi, one of the medical student leaders.
“We get patients who are there for back pain, for the flu, for uncontrolled diabetes, for hypertension, for rashes, for dental problems. We even get pediatric cases,” he said.
The students, under the guidance of faculty mentors, provide basic care and referrals, all at no charge.
“The point of the clinic is not to always have them come back to the clinic, because it’s an outpatient clinic,” Al-Asadi said. “The point is to treat them at that moment and try to get them linked to the health care system here in San Antonio. If they don’t qualify for the [Affordable Care Act], we try Carelink, a financial assistance health care program through University Health System. And usually we’re successful with that.”
Listening, learning, treating
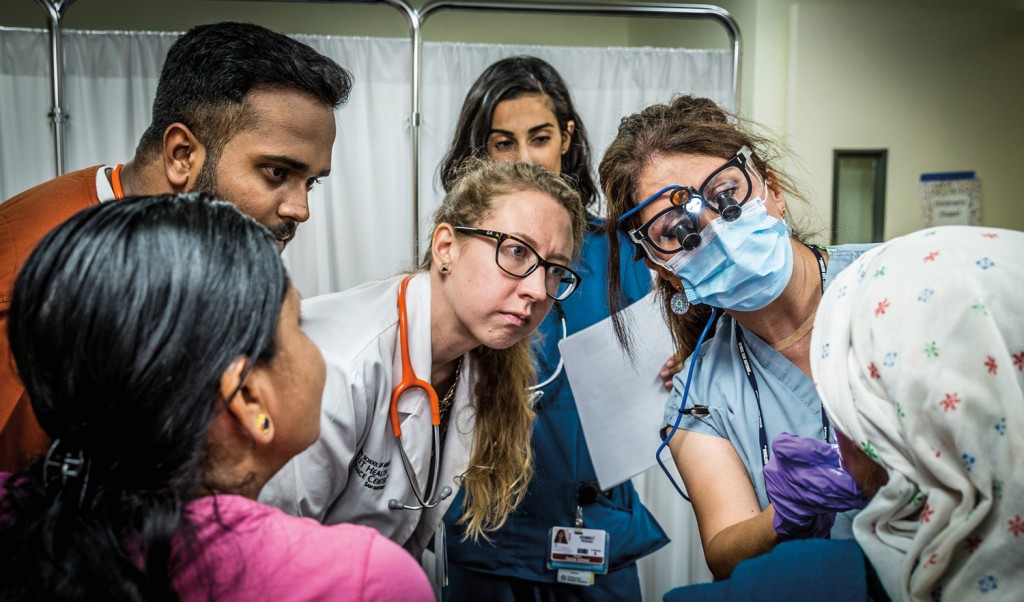
The refugee clinic provides unique challenges and opportunities for the future health care providers. One is the interprofessional nature of the setting. Teams are made up of a medical student, a nursing student and a dental student. They all observe each other’s role in the patient’s treatment and report as a team to their faculty advisers.
“I feel like I’m applying nursing school [lessons] even before I’ve graduated,” said Petty. “You learn the behind-the-scenes of a clinic, you learn how doctors interact with patients, how dentists interact. It’s all-encompassing. You get more information there than you’d get in a regular classroom.”
Students are able to learn from each other, said Peggah Hemmat, a fourth-year dental student and first-generation Iranian-American.
“As a dental student, I’ve learned so much about the medical aspect and how to interview patients and what questions to ask,” she said.
“I remember a patient who had periodontal disease, bone disease. And they had no idea what that was. We had to sit with them and explain why this is happening, what are some risk factors and how do we make sure you don’t lose all your teeth. Not only was it a learning experience for the patient, it was a learning experience for the nursing and medical students.”
A particular test for the students comes with the nature of the patient population itself.
“One of the greatest challenges is dealing with so many different cultures, so many different languages,” said Eden Bernstein, one of the medical student leaders. “We try to have adequate interpreters, but a lot of times we have to improvise and be very patient with the patients that we see. There’s not really an easy answer, it’s just kind of being resilient and focusing on the task at hand.”
Many of the students, as well as the faculty advisers, have some sort of international background or experience, and many are bilingual. There are Arabic speakers such as Al-Asadi, the medical student. Hemmat, the dental student, speaks fluent Farsi. Alizain Maneshia, a nursing student and native of Pakistan, speaks Hindi. Others speak French and Spanish.
In some cases, one member of a patient’s family speaks enough English to translate. But still, at times, interpreters have to be hired. Aside from the language differences, many refugees have had little experience with health care and find it difficult to describe symptoms or illness progression.
[bgsection pex_attr_title="" pex_attr_subtitle="" pex_attr_undefined="undefined" pex_attr_style="section-dark" pex_attr_bgcolor="000000" pex_attr_image="" pex_attr_imageopacity="1" pex_attr_bgimagestyle="static" pex_attr_titlecolor="ffffff" pex_attr_textcolor="ffffff" pex_attr_height="150"]
You don’t have to do mission trips in another country to learn about the world.
The world is here in San Antonio.”
—Moshtagh R. Farokhi, D.D.S., M.P.H., clinical assistant professor in comprehensive dentistry and dentistry adviser for the Refugee Health Clinic
[/bgsection]
Stepping out of the box
If the cultural challenges are steep, the gratification is abundant, the students agreed.
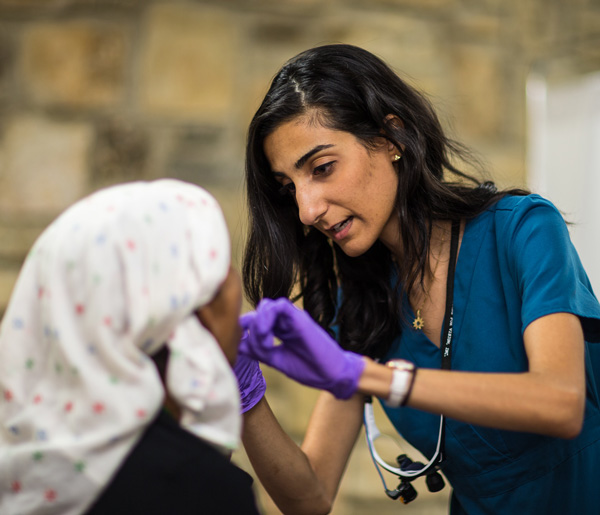
“Every time I leave the refugee clinic, I know that I’ve impacted this population just a little bit more,” Hemmat said. “Every one of these cultures is very family oriented. So if you tell them just a little about oral hygiene or teach them how to take care of their teeth, it will permeate through the rest of their [family circle].”
Bernstein, the medical student, contrasted his experiences at the clinic with classroom work.
“Going through the curriculum for the first years of medical school—it’s the preclinical medicine where we focus on the disease process, on the science,” he said. “It’s very textbook-oriented learning. So any time that I’m able to step out of that little box and glimpse what I’ll eventually see as a doctor and how I can potentially make an impact in the future, it’s invigorating and exciting.
“Every once in a while I see a patient and I’ll refer them out to receive care from a different place or we send them to get labs at University Hospital, and we follow them up at the next clinic and I see that the treatment that we gave them worked and they’re better. It’s very refreshing to feel that you’ve made this impact.”
Petty, the nursing student, pointed to the inherent altruism in health care fields.
“I wanted to be a nurse because I like pus and broken bones and blood,” she said, only half-jokingly. “And it’s exciting. And at the end of the day, whether it’s something as outrageous as that or something as simple as helping a Nepalese man to overcome the flu at our clinic, you’re helping someone.”
Al-Asadi remembers a refugee who came to the clinic suffering from severe anemia. He was able to diagnose it and get her the proper treatment.
“I felt happy,” he said, “because I thought that was the gratification I was looking for. To make people feel better and to feel gratified, I think that’s part of the payment. It’s not necessarily financial. It’s a humanitarian profession, and we all signed up to serve people. And we should keep that always in sight.”

Waist not
Diet sodas linked to waist gain
You could search all day in Sharon Fowler’s kitchen and pantry and there’s one thing you’d never, ever find: diet soda.
“Absolutely not,” said Fowler, M.P.H., adjunct faculty in the School of Medicine at the Health Science Center.
Fowler was the lead author of a paper published in the Journal of the American Geriatrics Society that described how consuming diet sodas was linked to subsequent increases in waist size among people 65 and older: The more diet sodas they drank, the more their waist size grew over the next decade. Data for the study came from the San Antonio Longitudinal Study of Aging (SALSA), led by Helen P. Hazuda, Ph.D., senior author and professor of medicine at the Health Science Center. Ken Williams, M.S., P.Stat., adjunct faculty in the Long School of Medicine, co-authored the paper and performed all analyses reported in it.
“There’s a heated debate about whether this is a causal relationship,” Fowler said. “It’s my personal opinion that it is.”
One of the explanations is that the artificial sweeteners themselves affect the metabolism, Fowler explained. If a person tastes something sweet, it’s not just the brain that absorbs the information; so do other parts of the body. When the body registers sweetness, it ramps up to deal with sugar. But if there isn’t real sugar present, the body doesn’t know how to handle it.
“It’s kind of like crying wolf,” she said, and can lead to metabolic dysregulation.
To make matters worse, Fowler said, one of the most dangerous places you can gain weight is your middle, because increasing waist size is linked to increasing visceral fat and an increase in inflammation, which is tied to the increased risk of arthritis, diabetes, cancer, heart attack, Alzheimer’s disease and other major medical problems.
What’s next for Fowler? She’s currently pursuing her doctorate in epidemiology and plans to continue her research on artificial sweeteners.
“What I am most concerned about is when women are pregnant and they’re using diet sodas, or consuming artificial sweeteners in other ways,” she said. “What is happening to their unborn child? There are a number of people who have reported neurological problems when they themselves have taken certain artificial sweeteners—brain fog, memory loss. I want to look at whether the unborn child is at increased risk of developing neurological problems when the mother has been exposed to artificial sweeteners. To me, that would be infinitely worse than gaining or losing a few pounds.”

Drawing it out

and an alumna of the School of Nursing.
Zyren Lopez just can’t tolerate cats. “Cats and dust,” he said in a polite whisper.
In the second grade, Zyren recalled, “I started getting really sick. My chest was hurting and it was hard to breathe, so I went to the nurse and she called my mom. And they wanted to take me to the doctor. They wanted to rush me to the hospital.”
Zyren was soon diagnosed with asthma, a chronic lung disease that inflames and narrows the airways, making it hard to breathe. Asthma affects one in 10 people, including an estimated 7 million children in the United States.
Now 11 and soon to be a fifth grader at Driggers Elementary on San Antonio’s northwest side, Zyren considers himself a normal kid, albeit one who must be aware of symptoms and triggers and who takes daily long-term asthma control medications.
“I am a registered respiratory therapist certified in asthma education and I’m an artist. I believe Asthma2Art is a great way for children to express what it feels like to live with asthma,” said Hart, assistant professor and director of clinical education in the Department of Respiratory Care in the School of Health Professions.
The program for children who have already been diagnosed with asthma has two components, Hart explained: education and artistic expression. First, she and a respiratory care team go to a school and provide asthma management education to the students with asthma. Three education stations are set up for the students to rotate through during the program, each focused on a different subject.
“The ‘What is Asthma?’ station teaches the students how the lungs work and signs and symptoms of asthma,” Hart said. “Another station is focused on asthma triggers. Students identify their own asthma triggers, how these triggers make their asthma worse, and which triggers can cause them to have an asthma attack.”
Common triggers include allergens such as pollen, dust mites, cockroach droppings and mold, she said. Frequently, triggers are in the schools themselves, where carpeted libraries and stacks of books can gather dust mites, and water leaks in the ceiling or beneath sinks can accumulate mold.
After the stations comes the art.
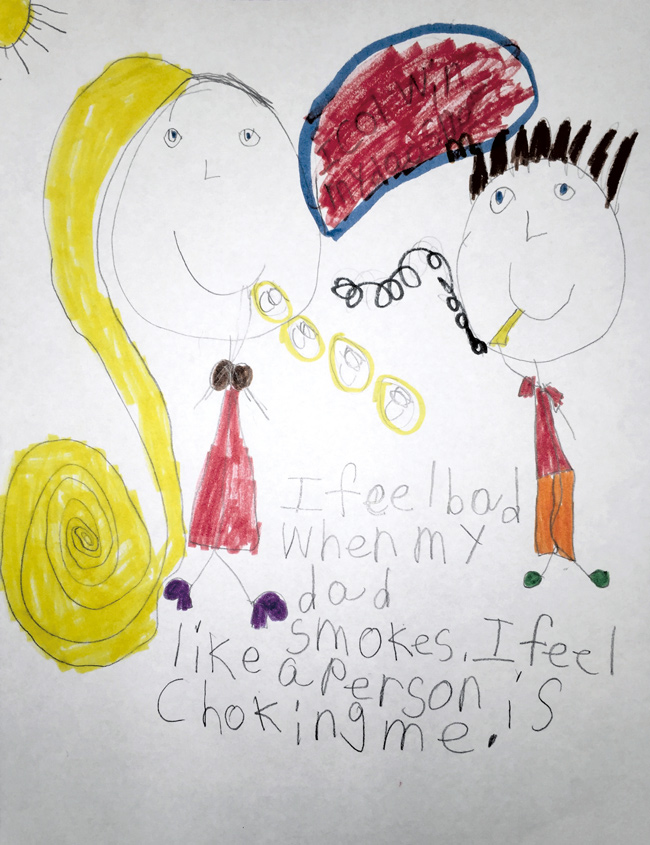 “Some kids choose to draw pictures of what triggers their asthma,” Hart said. “Others draw pictures of being totally isolated indoors and unable to go outside with friends, because that’s the way they’ve lived. The pictures I most enjoy seeing are the ones they create of them participating in the fun activities they enjoy when their asthma is controlled.”
Kathryn Cruz, RN, is the school nurse at Driggers Elementary and an alumna of the Health Science Center’s School of Nursing. About 100 of Driggers’ 640 students have been diagnosed with asthma, and most participated in the Asthma2 Art program in January, she said. Cruz called the artwork the students created meaningful and amazing.
“One child [expressed] that during an asthma attack it felt like barbed wire, just very tight and painful on his chest,” Cruz said. “Another little girl who was a second grader drew a very nice picture of her and her dad there in a house, and the dad was smoking, and she said, ‘Dad, please stop smoking. I can’t breathe.’ And I was just very taken aback by that.”
Tobacco smoke is especially bad for kids who have asthma, Hart said.
“It’s very important for adults to know that just being around someone after they have smoked a cigarette can trigger an asthma attack. Even emotions such as crying hard or laughing can trigger asthma,” she said.
Since children spend most of their days in school, Hart and her team surveys the physical condition of the school and identifies potential asthma triggers. They recommend ways to maintain asthma-friendly classrooms and train teachers and staff to recognize signs and symptoms of asthma and respond properly to a child having an asthma attack.

“During the cold and flu season, lots of children come to class coughing and with runny noses, both classic warning signs of asthma,” she said. “Knowing in advance which children in the classroom have asthma may reduce the risk of an emergency situation. Otherwise, it may be missed.
“There are tragic instances where a child has died at school from an asthma attack. It was either not recognized as an emergency or the school did not have the medication readily available to treat the child soon enough. Having asthma action plans in place for the school to follow for each child and having school staff trained in asthma emergency management is key to preventing this from ever happening here in our schools.”
Asthma2Art allows students, like Zyren, to articulate their fears and frustrations about the disease. Indeed, art therapy has proven to decrease anxiety and increase quality of life for children with persistent asthma, according to a study from National Jewish Health. To date, six San Antonio schools have participated in Asthma2Art aided by a grant from the Environmental Protection Agency.
Zyren, who wants to be an artist, said he enjoyed drawing a dreaded cat in the Asthma2Art program “because I could tell what’s going on with my asthma.”
All artwork is judged by local artists and the winning artwork is published in a calendar.
“We’ve seen incredible pictures that speak louder than words, very emotional pieces describing what it feels like to live with asthma,” Hart said. “We are hoping through Asthma2Art to raise asthma awareness and offer tips to others about managing their asthma better.”

Professor emeritus continues life’s work through endowment
 Rajam Ramamurthy, M.D., may have been born and raised in India, but she’s grown fond of a particular American idiom.
“I believe you should put your money where your mouth is,” she says flatly.
Dr. Ramamurthy, professor emeritus in pediatrics, has a long history of giving back financially to the Health Science Center, where she has worked since 1977. Her latest gift of $100,000 established the Dr. Rajam Ramamurthy Endowment in Neonatology to support educational activities related to research on prematurity and premature infant care.
As a renowned neonatologist, Dr. Ramamurthy’s endowment is a continuation of her life’s work.
“When I took over the premature infant development clinic in 2000, one of the things I felt was that there was no educational activity in San Antonio or in most of South Texas for professionals who are helping these infants, such as physical therapists, speech therapists, occupational therapists, even physicians, pediatricians,” she said.
Once discharged from the neonatal intensive care unit, premature babies “were put in the mix of normal, full-term newborns…But these babies are extremely vulnerable, very delicate, and at least for the first few years of their lives they need very specialized, developmental care.”
The endowment will be used to educate those in the region about the importance of specialized care for premature infants. To that end, a portion of it was used to host the university’s first Rajam Ramamurthy Lectureship in Premature Infant Development in February, which featured Tonse Raju, M.D., medical officer of the National Institute of Child Health and Human Development in the National Institutes of Health.
The Ramamurthy family began giving to the university in 1996. In that time, their donations have surpassed $154,000, and have supported various university initiatives and programs including student scholarships and endowments for research and education. In 2013, the family created the Dr. Somayaji Ramamurthy Professorship Fund in Pain Management, named for Dr. Rajam Ramamurthy’s husband, Somayaji Ramamurthy, M.D., a professor of anesthesiology.
Faculty gifts are an especially powerful example of philanthropy because of what they already contribute to the university in their time and brainpower, said William L. Henrich, M.D., MACP, president of the Health Science Center.
“Our faculty is the engine that drives the missions of our university, and giving fuels the engine,” he said. “They see firsthand the impact of what is accomplished here, and they know the difference gifts can make. It is inspiring to see faculty invest in the future of our university through their own philanthropy.”
Faculty, by and large, do not amass great wealth, Dr. Rajam Ramamurthy said. Giving back takes a commitment. The first family endowment began on her and her husband’s 25th wedding anniversary when they asked their friends to forgo giving gifts and buy artwork instead, the proceeds of which funded the endowment.
“Gifts like these help us all see the good one person—one family—can do,” Dr. Henrich said.
Although retired, Dr. Rajam Ramamurthy plans to continue research in prematurity and stay involved at the Health Science Center. And she’ll keep on giving.
“My experience is you need to support things you believe in,” she said. “And it’s very important to do these kinds of activities so that these efforts can be sustained.”